PRATINYA BODANAPU / OPINION EDITOR
In the 1820s, poet Lord Byron reportedly drank vinegar and water and severely restricted his diet in pursuit of thinness. By the early 20th century, Americans were sold “reducing soaps” that promised to wash away fat. Later came vibrating belts meant to shake fat off the body, cigarettes marketed as an alternative to sweets and an endless succession of diet pills, meal replacements, cleanses and detox teas.
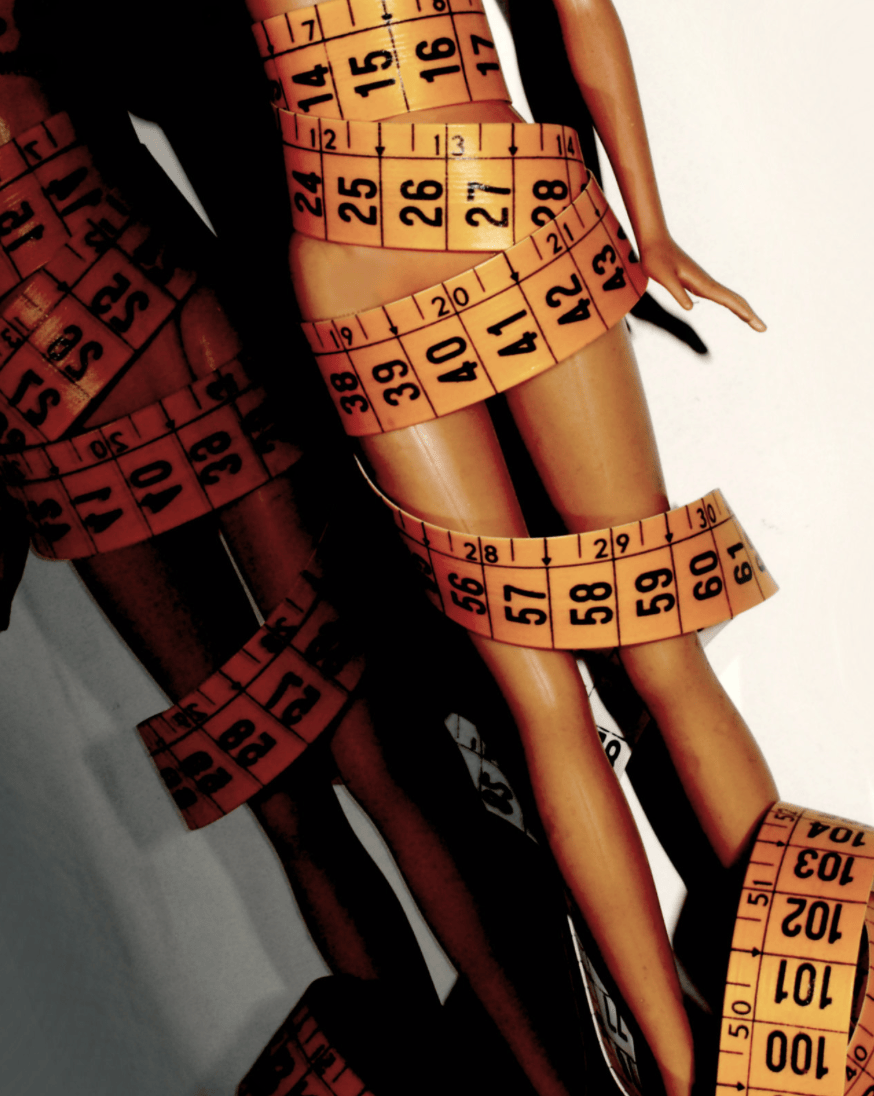
Over centuries, methods have changed, but the promise sold to us—that our bodies can and should be changed to fit the ideal of the moment—has remained the same.
Glucagon-like-peptide-1 medications, commonly known as GLP-1 drugs, emerged from decades of research beginning in the 1980s — transforming the treatment of Type 2 diabetes and, later, obesity.
More recently, names like Ozempic, Wegovy and Mounjaro have moved beyond doctor’s offices and into advertisements, celebrity interviews and social media feeds.
GLP-1s represent a new peak in a much older effort to capitalize on bodies and insecurities.
The ultimate question is not whether these medications should exist, but asking what happens when an extraordinarily effective medical treatment enters a market that has spent centuries learning how to monetize off self-doubt.
Data from advertising tracking firm MediaRadar showed that, during the first nine months of 2025, Novo Nordisk spent approximately $316 million advertising Wegovy in the United States and another $169 million advertising Ozempic. Drug manufacturing company Eli Lilly spent approximately $131 million advertising Zepbound and $83 million advertising Mounjaro during the same period.
Together, advertising for those four drugs approached $700 million in nine months. Their revenues are substantially larger. Eli Lilly surpassed $1 trillion valuation last year while Novodisk generated $9.16 billion in quarterly sales.
According to Harvard health, the U.S. and New Zealand are the only two countries that permit prescription drug companies to advertise directly to consumers. That means individuals living in these countries are more likely to encounter medications through television commercials, social media or pop culture before discussing them with a physician.
Celebrity discussion has accelerated that visibility. Amy Schumer stated on an episode on Watch What Happens Live with Andy Cohen that she lost weight on Ozempic, but severe nausea left her bedridden and unable to play with her son. Schumer’s experience complicates the way GLP-1 transformations are presented in popular culture as smaller bodies are visible on screens but the medical experience behind it often is not.
As GLP-1s have become increasingly popular in pop culture, their use has grown alongside the attention. A 2025 Kaiser Family Fund (KFF) poll found that 12% of U.S. adults were taking a GLP-1 medication, including 45% of adults diagnosed with diabetes and 23% of those who reported being diagnosed as overweight or obese. Morgan Stanley Research estimates that the global market for obesity and Type 2 diabetes treatments could reach $190 billion by 2035, more than twice its estimated size in 2025.
There are good medical reasons for that growth. According to a 2024 study conducted by the Centers for Disease Control and Prevention, every U.S. state and territory had an adult obesity prevalence of at least 25%. GLP-1 medications have also demonstrated benefits beyond weight loss showing results reducing cardiovascular death by 20%. For these patients, GLP-1’s prove to be necessary healthcare —treating chronic diseases.
That distinction matters because criticism of GLP-1 culture can easily become criticism of the people taking these medications while overlooking their primary purpose and the positive impacts they make on societies.
Simultaneously, acknowledging the medical value of GLP-1 drugs does not require ignoring the culture developing around them.
It is clear through the historic data being presented that human bodies have consistently been looked at as trends to capitalise off of, rather than being appreciated as the very things that keep us alive.
The rise of GLP-1 medications is particularly relevant to college students. A national study led by researchers at the University of Michigan examined prescription dispensing data from 2020 to 2023 covering 92% of U.S. pharmacies and found a 594% increase in the monthly number of adolescents and young adults ages 12 to 25 using GLP-1 medications. Among young adults agesd 18 to 25 (an age group that encompasses most traditional college students) use increased 659% among women and 481% among men. Author of the study, Kao-Ping Chua, also documented increased dispensing of Ozempic among young people, despite the drug not being approved for weight management in adolescents.
There is no number on a scale that neatly separates health care from beauty culture, and telehealth has made that boundary even more difficult to see. While online providers can expand access to obesity treatment, their rapid growth has created opportunities for aggressive marketing.
In 2025, the Federal Trade Commission took action against telehealth company NextMed, alleging that it used deceptive weight-loss claims, fake reviews, misleading before-and-after images and unclear pricing to market GLP-1 weight-loss programs. The FDA subsequently issued warning letters to 30 telehealth companies in March 2026 over allegedly false or misleading claims involving compounded GLP-1 products. These cases do not mean telehealth
GLP-1 prescribing as a whole is unsafe. They illustrate what can happen when an intensely desired physical transformation becomes commercially valuable.
The GLP-1 boom has also created a strange contradiction: Americans are increasingly exposed to a body standard that pharmaceutical science can help achieve, while access to that science remains heavily dependent on income and insurance coverage.
According to 2025 KFF poll, 56% of people who had used GLP-1 medications said they found them difficult to afford, including 55% of insured users. Among insured users, 27% reported paying the entire cost themselves—14% cited cost and 13% cited side effects.
Rapidly increasing demand has also periodically strained supply. Wegovy, Mounjaro and Zepbound have experienced shortages as manufacturers attempted to keep pace. This scarcity prompted criticism of people using the medications solely for weight loss while patients with diabetes struggled to fill prescriptions.
These shortages reveal how quickly the consequences of a cultural phenomenon can become a medical crisis.
What begins on television screens and social media feeds eventually reaches doctors’ offices, insurance companies and pharmacies.
Moreover, with millions of people using these medications, larger questions about their long term and side effects also come to play. GLP-1 drugs are not untested because the drug class has been used in diabetes treatment for years, and medications such as semaglutide have been evaluated in large clinical trials. Their known risks and common side effects are well documented, particularly gastrointestinal effects.
What we cannot yet have is decades of evidence for the newest drugs being used at today’s scale, particularly when individuals are using these drugs for reasons that do not pertain to diabetes. Questions of long-term use, decreasing muscle mass and weight regain are ones that scientists do not have firm responses on because of how new the use of GLP-1s is in the weight loss space.
Ozempic was approved by the FDA in 2017. Wegovy followed in 2021 and Zepbound in 2023. No study can give us 20 years of evidence on a medication that has not been used for 20 years in its current indication. That uncertainty does not justify withholding effective treatment from patients who need it, but should complicate the casualness with which these medications are being discussed.
For generations, people have swallowed, smoked, sweated and starved themselves trying to make their bodies conform to the ideal of their time. History should make us skeptical of the idea that our desire to change our bodies exists independently of the industries offering to change them. The ideal body changes, but there is almost always money to be made from the distance between the body someone has and the body they are told they should want.
GLP-1 medications are not inherently good or bad. However, it is important to make well informed decisions and, as long as billions of dollars depend on the answer, we should pay attention to who is trying to decide on our behalf.
The Weight of a trend – Photo courtesy of giovanna baldini on Flickr



 The USD Vista

Leave a comment